Shoulder Pain · Faithful Fields · Kilcormac · Co. Offaly

Shoulder Pain Treatment

Expert shoulder assessment, treatment and rehabilitation at Offaly Physio & Performance Lab — restoring pain-free movement and strength.

Assessment-led care Hands-on + rehab Return-to-activity focus
6 Common Shoulder conditions we treat
5+ Evidence-based techniques
1 Integrated plan for you

The Most Mobile Joint In The Body

Understanding Shoulder Pain

The shoulder is the most mobile joint in the human body, achieving its remarkable range of movement through a complex interplay of joints — the glenohumeral, acromioclavicular and scapulothoracic — and an intricate network of soft tissue structures including the rotator cuff, labrum, capsule and scapular stabilisers. This mobility comes at the cost of stability, making the shoulder vulnerable to a wide range of injuries and conditions.

At Offaly Physio & Performance Lab, we take a comprehensive approach to shoulder pain. Our physiotherapists combine hands-on treatment, exercise rehabilitation and adjunct therapies to address not only your symptoms but the underlying factors contributing to your shoulder problem. Whether you are dealing with a sports injury, a gradual onset condition or post-surgical rehabilitation, we will develop an individualised treatment plan to help you regain pain-free function.

From a fall on the pitch to a pain that crept in gradually — we treat the cause, not just the symptoms, with a plan built around your goals.

What We Treat

Shoulder Conditions We Treat

We assess and treat a wide range of shoulder conditions, including:

Glenohumeral joint instability assessment

Glenohumeral Joint Instability

Shoulder instability ranges from traumatic dislocation to micro-instability and atraumatic instability. It can involve labral damage, capsular laxity or muscle patterning issues affecting the control of the shoulder joint.
ACJ sprain treatment

ACJ Sprain

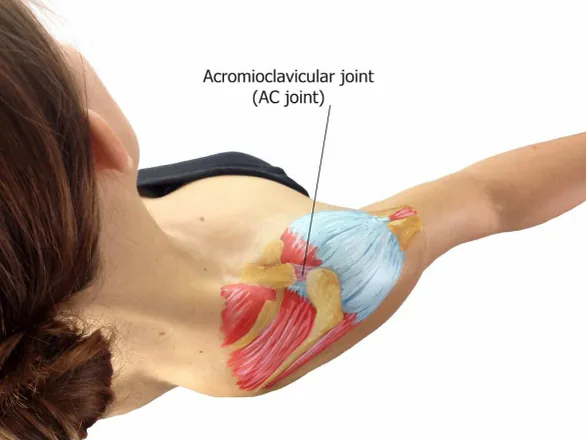
Injury to the acromioclavicular joint, commonly from a fall onto the point of the shoulder or direct impact. Ranges from mild sprain to complete rupture of the coracoclavicular ligaments — frequently seen in contact sports.

Frozen shoulder treatment

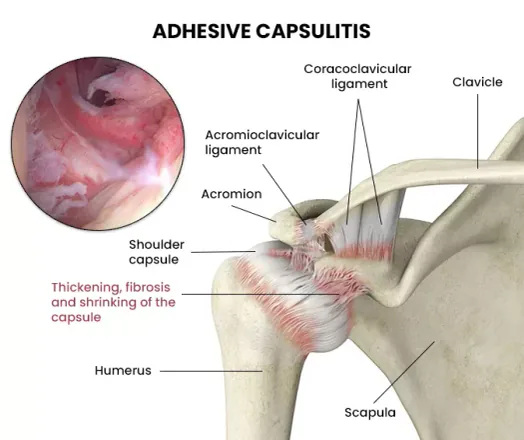
Frozen Shoulder (Adhesive Capsulitis)

A condition where the shoulder capsule becomes inflamed and then fibrosed, leading to marked loss of range of movement and significant pain. Progresses through freezing, frozen and thawing phases.

Shoulder impingement treatment

Shoulder Impingement

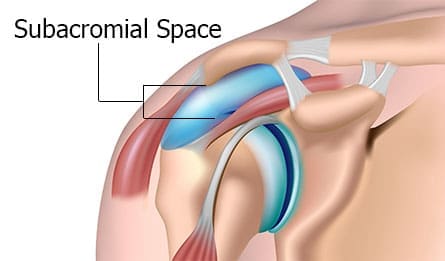
Primary (subacromial) impingement involves structural narrowing of the subacromial space, while secondary impingement is caused by functional factors such as rotator cuff weakness and poor scapular control. Subcoracoid impingement can also occur.

Rotator cuff tendinopathy rehabilitation

Rotator Cuff Tendinopathy

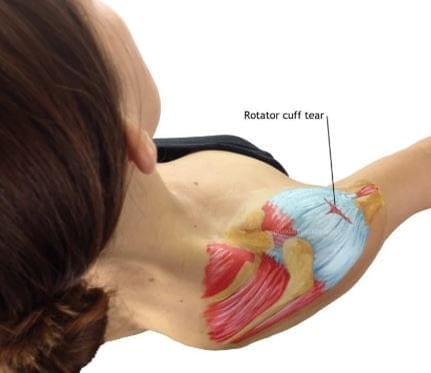
Degeneration or tendinopathy of the rotator cuff tendons, most commonly supraspinatus. Can cause pain, weakness and contribute to secondary impingement. Partial and full thickness tears can occur, especially in older populations.

Scapular dyskinesis rehabilitation

Scapular Dyskinesis

Abnormal movement and position of the scapula during arm movement. The scapula is the foundation of shoulder function, and poor scapular control can contribute to impingement, instability and rotator cuff problems.

Condition 01

Glenohumeral Joint Instability

Shoulder instability encompasses a spectrum of problems ranging from traumatic dislocation — where the humeral head is forced out of its socket — to micro-instability and atraumatic instability. Traumatic dislocation often results in damage to the labrum (Bankart lesion) or the bony architecture of the glenoid. SLAP (Superior Labrum Anterior and Posterior) lesions can also occur, affecting the attachment of the biceps tendon to the labrum. Atraumatic instability may involve capsular laxity, generalised joint hypermobility, or muscle patterning issues where altered muscle activation contributes to the sensation of instability.

Treatment Approach

  • Hands-on treatment with motor control retraining of the rotator cuff and scapular stabilisers
  • Progressive strengthening and a structured return-to-activity programme
  • Clinical Pilates as part of the motor control approach for many patients with instability
  • Performance testing for objective assessment of shoulder readiness before return to sport
  • Referral for a surgical opinion where appropriate — particularly after traumatic dislocation in younger athletes or when conservative management has not succeeded

Condition 02

ACJ (Acromioclavicular Joint) Sprain

An ACJ sprain is an injury to the acromioclavicular joint, most commonly caused by a fall onto the point of the shoulder or a direct impact to the joint. The severity ranges from a mild sprain of the acromioclavicular ligament to a complete rupture of the coracoclavicular ligaments, which can result in visible deformity at the top of the shoulder. ACJ sprains are common in contact sports such as rugby, GAA and martial arts, as well as in cycling falls.

Treatment Approach

  • Hands-on treatment and joint mobilisations
  • Taping to support the joint
  • Progressive strengthening and return-to-sport programme
  • Performance testing to ensure the shoulder is ready for the demands of contact sport
  • Referral for a surgical opinion in severe cases with significant displacement or persistent symptoms

Condition 03

Frozen Shoulder (Adhesive Capsulitis)

Frozen shoulder, or adhesive capsulitis, is a condition where the shoulder capsule becomes inflamed and then progressively fibrosed, leading to a marked loss of range of movement and significant pain. The condition typically progresses through three phases: the freezing phase (increasing pain and progressive stiffness), the frozen phase (marked stiffness with less pain), and the thawing phase (gradual recovery of movement). Frozen shoulder can be primary (idiopathic, with no clear cause) or secondary (following injury, surgery or prolonged immobilisation). It is more common in people with diabetes and those aged between 40 and 60.

Treatment Approach

  • Hands-on treatment and joint mobilisations to restore range of movement
  • Pain management strategies
  • Progressive stretching and strengthening tailored to the phase of the condition
  • Injection therapy — an intra-articular corticosteroid injection can be very effective in the painful freezing phase, reducing inflammation so rehabilitation can progress more comfortably

Condition 04

Shoulder Impingement

Shoulder impingement refers to the compression of soft tissue structures within the shoulder during movement. There are several types:

Primary Impingement (Subacromial)

Primary impingement involves structural narrowing of the subacromial space, often due to acromial morphology (such as a hooked acromion), bony spurs, or a thickened subacromial bursa. The rotator cuff tendons and subacromial bursa become compressed during overhead movements, leading to pain, inflammation and potential tendon damage over time.

Secondary Impingement

Secondary impingement is caused by functional narrowing of the subacromial space. This is the more common type and is very responsive to rehabilitation. It typically results from rotator cuff tendinopathy — where weakness and poor control of the cuff muscles allows the humeral head to ride up under the acromion — combined with poor scapular control and altered movement patterns. Addressing these functional factors through targeted rehabilitation can significantly improve symptoms.

Subcoracoid Impingement

Subcoracoid impingement involves compression of the subscapularis tendon and the long head of the biceps tendon between the coracoid process and the lesser tuberosity of the humerus. This less common form of impingement can cause anterior shoulder pain and requires careful assessment to distinguish it from other causes.

Treatment Approach

  • Hands-on treatment, joint mobilisations, and motor control and strength training to improve global shoulder function
  • Particular emphasis on rotator cuff and scapular control, along with posture correction
  • Shockwave therapy for tendon-related components of impingement
  • Injection therapy — subacromial corticosteroid injection can reduce inflammation in selected cases
  • Clinical Pilates to retrain optimal shoulder and scapular movement patterns

Condition 05

Rotator Cuff Tendinopathy

Rotator cuff tendinopathy refers to degeneration or tendinopathy of the rotator cuff tendons, most commonly the supraspinatus tendon. The condition follows the tendinopathy continuum — from reactive tendinopathy through dysrepair and degenerative change — and can cause pain, weakness and functional limitation. Rotator cuff tendinopathy is a common contributor to secondary impingement, as weakness and poor control of the cuff muscles allows the humeral head to migrate superiorly during overhead activities. Partial and full thickness tears can occur, particularly in older populations where degenerative changes are more prevalent.

Treatment Approach

  • Progressive tendon loading and careful load management
  • Addressing the biomechanical factors contributing to the tendinopathy — including scapular control, posture and movement patterns
  • Shockwave therapy for persistent tendon pain
  • Injection therapy to reduce pain and inflammation in selected cases, to facilitate rehabilitation
  • The goal: restore tendon capacity and shoulder function through a structured, progressive rehabilitation programme

Condition 06

Scapular Dyskinesis

Scapular dyskinesis refers to abnormal movement and position of the scapula during arm movement. The scapula is the foundation of shoulder function — it provides the stable base from which the arm operates and serves as the attachment site for numerous muscles. When scapular control is compromised, it affects the entire shoulder complex and can contribute to impingement, instability and rotator cuff problems. Scapular dyskinesis is often related to weak or inhibited serratus anterior and lower trapezius muscles, a tight pectoralis minor, and poor postural awareness. Thoracic and cervical spine issues can also contribute to scapular and shoulder problems, which is why we may also assess the spinal pain contribution to your shoulder symptoms.

Treatment Approach

  • Hands-on treatment to restore thoracic and scapular mobility
  • Motor control retraining to improve the coordination and timing of scapular muscle activation
  • Strengthening of the scapular stabilisers — particularly serratus anterior and lower trapezius
  • Postural education
  • Clinical Pilates to develop the body awareness and control needed for optimal shoulder function

Matching Cause To Care

Our Approach — Linking Pathologies with Treatments

We match each shoulder condition with the most appropriate combination of treatments. Here is how we link common shoulder pathologies with their treatment pathways:

Glenohumeral Instability

Motor control retraining of the rotator cuff and scapular stabilisers, Clinical Pilates, progressive strengthening, and performance testing for return to sport.

ACJ Sprain

Joint mobilisations, taping, progressive strengthening, and performance testing for return to sport.

Frozen Shoulder

Joint mobilisations, injection therapy (corticosteroid in the freezing phase), progressive stretching and strengthening.

Scapular Dyskinesis

Motor control retraining, Clinical Pilates, postural education, and spinal assessment including spinal pain evaluation.

The Kinetic Chain

A Comprehensive Approach to Shoulder Pain

One of the most important principles at Offaly Physio & Performance Lab is that shoulder pain should not be treated in isolation. The shoulder does not function alone — it is part of a complex kinetic chain involving the cervical and thoracic spine, the scapula, the ribcage and the core. Factors that can contribute to shoulder pain include:

  • Reduced rotator cuff strength and endurance
  • Poor scapular control and dyskinesis
  • Thoracic stiffness and postural issues
  • Cervical spine referred pain
  • Training load errors and sudden increases in activity
  • Biomechanical factors and movement compensations
  • Inadequate warm-up or recovery
  • Return to sport following injury

Our aim is not simply to reduce symptoms — it is to help you regain the shoulder function and capacity required for work, sport and daily life.

Why Choose Us

Why Choose Offaly Physio for Shoulder Pain?

Offaly Physio & Performance Lab provides physiotherapy, sports rehabilitation and performance services from our clinic in Tullamore, County Offaly. Our approach combines thorough clinical assessment with progressive rehabilitation and, where appropriate, objective strength and performance testing.

Our Shoulder Pain Service Includes:

  • Assessment by an experienced clinician
  • Individualised treatment planning
  • Hands-on treatment and joint mobilisations
  • Motor control and scapular retraining
  • Progressive strengthening and tendon loading
  • Access to shockwave therapy and injection therapy where appropriate
  • Clinical Pilates for motor control and postural retraining
  • Return-to-sport planning and performance testing
  • Clear advice regarding activity and training load

Rather than simply treating the painful area, we aim to identify the factors contributing to your shoulder problem and develop a plan to help you return to the activities that matter to you.

Common Questions

Shoulder Pain — FAQs

Book a Shoulder Pain Assessment 

If you are experiencing shoulder pain — whether from a recent injury, a gradual onset condition, or a persistent problem that has not fully resolved — we can help. Our clinic is based in Faithful Fields Kilcormac, Co. Offaly, providing physiotherapy and sports rehabilitation to patients and athletes from Offaly and across the Midlands.

Book an Appointment Online

Book A Time That Suits You

BOOK AN APPOINTMENT NOW BOOK AN APPOINTMENT NOW